
Quick answer: Thrush is a yeast infection (caused by Candida) that can affect a breastfeeding mum's nipples and her baby's mouth. The classic signs are burning nipple pain, especially after feeds, and white patches in baby's mouth that don't wipe off. But here's the thing many mums aren't told: nipple pain is much more often caused by latch, pump or flange problems than by thrush. So get it properly checked before you start treatment. And yes, you can keep breastfeeding.
What is thrush?
Thrush (also called candidiasis) is an overgrowth of Candida, a yeast that normally lives on our skin, in our mouths and in our gut without causing trouble. When the balance is upset, it can grow and cause soreness. In breastfeeding, it can show up on mum's nipples and areola, and in baby's mouth (oral thrush) or nappy area.
Things that can make thrush more likely include recent antibiotics (for mum or baby), cracked or damaged nipples, and baby having oral thrush or a thrush nappy rash.
If you or your baby get thrush, it doesn't mean you've done anything wrong. It's common and treatable.
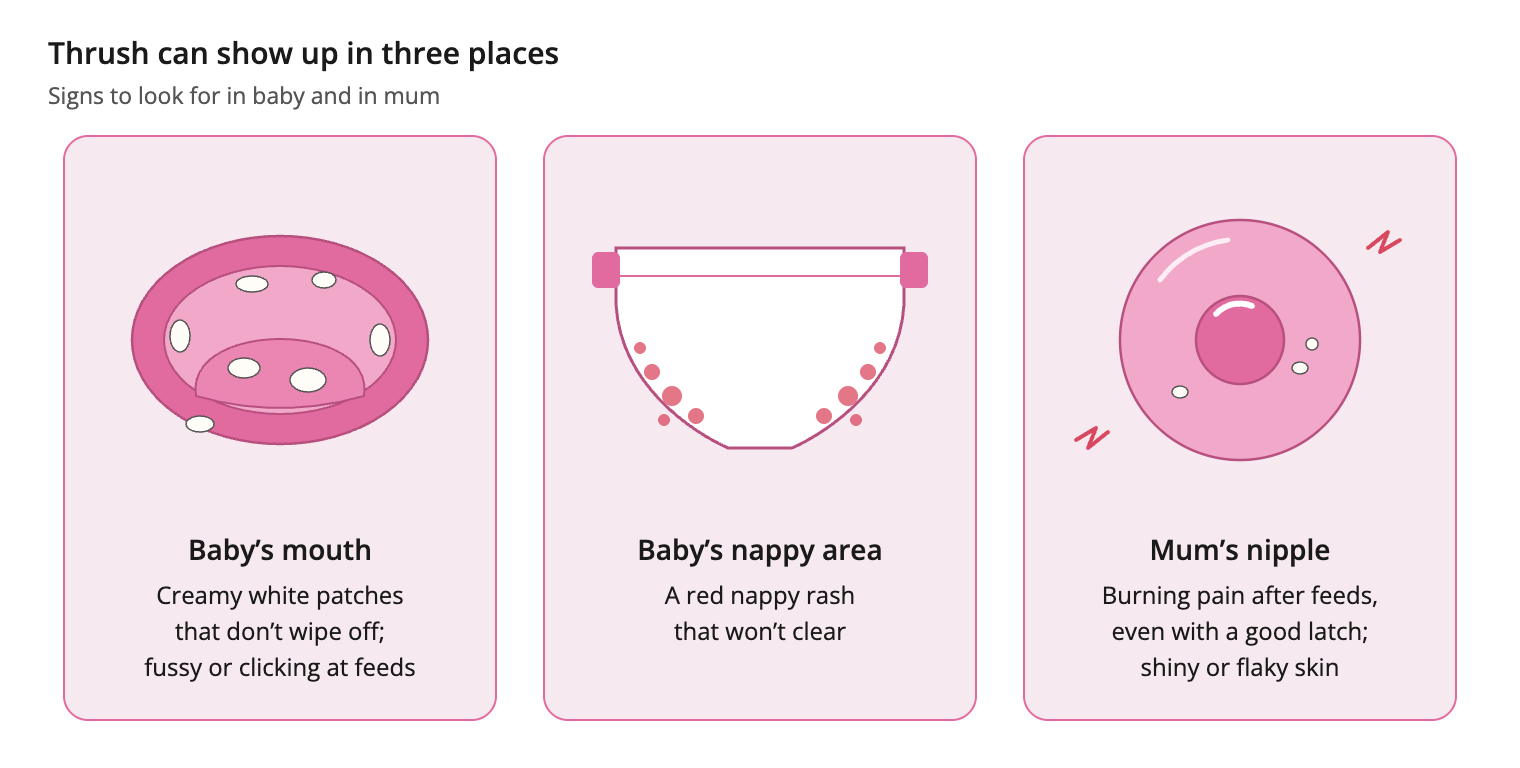
Signs of thrush in mum
Burning nipple pain, especially after every feed, even when the latch looks good
Itchy or very sensitive nipples
Shiny or flaky skin on the nipple or areola
White patches or tiny blisters on the nipple or areola
Loss of colour on the nipple or areola (harder to see on darker skin)
Cracked nipples that won't heal
Nipples with thrush can also look completely normal, which is one reason it's hard to diagnose by looks alone.
Signs of thrush in baby
Creamy white spots or patches on the tongue, gums, roof of the mouth or inside the cheeks that don't wipe off (milk residue usually wipes away)
A white film on the lips
Fussing, pulling off or clicking during feeds because the mouth is sore
A nappy rash that won't clear
Want to see what oral thrush looks like? There are clear photos on the NHS and Pregnancy, Birth & Baby websites. Unlike milk, thrush patches don't wipe off easily.
Some babies have thrush with no obvious signs at all.
What else could it be?
This is the part that matters most if your nipples are still sore. UNICEF UK's Baby Friendly Initiative now says breastfeeding pain used to be blamed on thrush too often, and that latch, pump suction, flange fit or tongue-tie are more likely causes. Several things can look or feel like thrush:
Latch or positioning: pain mainly during the feed; nipple looks squashed, slanted or white-tipped after. Who can help: an IBCLC.
Tongue-tie or baby's mouth or jaw: shallow latch, clicking, long feeds, poor weight gain. Who can help: an IBCLC, then a doctor if a tie needs assessing.
Pump suction or wrong flange size: pain or rubbing while pumping, nipple swelling. Who can help: an IBCLC (flange and suction check).
Vasospasm (nipple blanching): nipple turns white, then purple or red, after feeds or in the cold; throbbing or burning pain; cold hands and feet. Warmth helps; see a doctor if it persists.
Eczema or dermatitis: itchy, red, scaly or weepy skin; may react to creams, breast pads or detergent. Who can help: a doctor.
Bacterial infection of a cracked nipple: a crack that won't heal, yellow crust or pus, spreading redness. Who can help: a doctor.
Blocked duct or mastitis: tender lump or wedge, redness, feeling unwell or feverish. See a doctor if you have fever or flu-like symptoms.
More than one of these can happen at the same time. That's why a full assessment, not just a quick look, is the best first step.
What about deep, shooting breast pain?
You may read about "ductal thrush" or "breast thrush": deep, stabbing pain inside the breast. Honestly, experts don't agree on this. The Academy of Breastfeeding Medicine says there's no expert consensus on whether deep breast pain is caused by Candida, by bacteria, or by something non-infectious such as vasospasm. One Australian study did find Candida more often in mums with burning nipple pain plus breast pain (54% vs 36%). But it showed a link, not proof that yeast caused the pain. If you have deep breast pain, see a doctor and get your feeding checked, rather than assuming it's thrush.
Can I keep breastfeeding with thrush?
Yes. NHS guidance is to keep breastfeeding if you can. If it's too painful, express your milk and feed it to baby instead. The NHS also notes there's no current evidence that using your stored expressed milk causes thrush to come back.
What to do if you think you have thrush
Get your latch or pumping checked first. Many "thrush" cases turn out to be a latch, tongue-tie or flange problem, and antifungals won't fix those.
See your GP, polyclinic doctor or baby's paediatrician for a diagnosis. They may take a swab from your nipple and baby's mouth. Treatment is usually an antifungal cream for your nipples and an antifungal gel or liquid for baby. Your doctor will decide whether you both need treating.
Ask your doctor or pharmacist before using any medicine or cream while breastfeeding, including over-the-counter ones.
Help stop it spreading:
Wash your hands well, especially after nappy changes
Change breast pads often and let your nipples dry after feeds
Use separate towels
Sterilise dummies, teats and pump parts that touch milk
Wash bras, towels and baby's clothes on a hot wash, and change damp nursing bras
When to see a doctor quickly
You have a fever, chills or feel flu-like
Part of your breast is red, hot or swollen
A cracked nipple has pus, yellow crust or spreading redness
Baby is feeding poorly, has fewer wet nappies, or seems unwell
The pain is stopping you from feeding or expressing
How an IBCLC can help
An IBCLC (International Board Certified Lactation Consultant) looks at the whole picture. At a home visit we watch a full feed (and a pumping session if you pump), check baby's mouth, latch and suck, look at your nipples and breasts, and check your pump settings and flange fit. If it looks like thrush or another medical issue, we'll tell you who to see and what to ask. If it's a latch or pumping problem, we fix it together so feeding stops hurting.
Sore nipples that just won't settle? Book an IBCLC home visit. We come to you, island-wide across Singapore. Or see all consult options and prices.
Frequently asked questions
Can you breastfeed with thrush?
Yes. Keep breastfeeding if you can. If it's too painful, express and feed your milk to baby. NHS guidance says there's no current evidence that using your stored milk makes thrush come back.
What are the symptoms of thrush when breastfeeding?
In mum: burning nipple pain (often after feeds), itchy or sensitive nipples, shiny or flaky skin, white patches or loss of colour on the nipple or areola. In baby: white patches in the mouth that don't wipe off, a white film on the lips, fussing at the breast, or a nappy rash that won't clear.
What does thrush on nipples look like?
The skin may look shiny, flaky, pinker or paler than usual, sometimes with white patches or tiny blisters. Often it looks normal, so a check by a doctor or IBCLC is more reliable than looks alone.
What causes thrush when breastfeeding?
An overgrowth of Candida, a yeast that normally lives on skin and in the mouth. Recent antibiotics, damaged nipples and baby having oral thrush can make it more likely.
Can you get thrush in your breast?
Experts don't agree. Deep, shooting breast pain is sometimes called "breast" or "ductal" thrush, but the Academy of Breastfeeding Medicine says there's no consensus on whether yeast, bacteria or something else (like vasospasm) causes it. See a doctor and get your feeding checked.
Can you get nipple thrush without breastfeeding?
It's uncommon. A nipple rash or soreness when you're not breastfeeding is more likely to be something else, such as eczema. Any nipple change that doesn't settle within a few weeks should be checked by a doctor.
Why does my thrush keep coming back?
Often because it wasn't thrush in the first place. Ongoing nipple pain is commonly caused by latch, tongue-tie, pump suction or flange size. A full assessment by an IBCLC, plus your doctor, is the best way to find the real cause.
References
Thrush and breastfeeding, NHS Start for Life.
Information sheet on thrush, UNICEF UK Baby Friendly Initiative, April 2025.
Berens P, Eglash A, Malloy M, Steube AM. ABM Clinical Protocol #26: Persistent Pain with Breastfeeding. Breastfeeding Medicine, 2016;11(2).
Amir LH, Donath SM, Garland SM, et al. Does Candida and/or Staphylococcus play a role in nipple and breast pain in lactation? A cohort study in Melbourne, Australia. BMJ Open, 2013;3(3):e002351.